Parents need more than a surgeon and an operating date: they need clear information, reliable updates, practical help and a safe plan for feeding and recovery. By the end, you will know what to ask at each stage, how to judge a hospital’s family-support system and which details must be written down before you leave.
Key takeaways
- Ask for a confirmed diagnosis, treatment plan and named hospital contact at referral.
- Confirm who coordinates appointments, tests, admission and updates during the operation.
- Ask how breathing, monitoring, pain relief and feeding will be managed in ICU.
- Leave with medication instructions, warning signs, follow-up dates and emergency contact numbers.
What support should begin when your baby is referred?
Support should start at referral, not on the morning of surgery. The hospital should move you from a referral note to a confirmed diagnosis, written treatment plan and named contact.
The paediatric cardiologist explains the anatomy and tests; the paediatric cardiac surgeon discusses repair; the cardiac anaesthetist covers anaesthesia and lines; and the neonatal or paediatric intensivist explains intensive care.
1. Ask for the exact diagnosis, the proposed operation or catheter procedure, its purpose, alternatives, major complications, expected ICU and total hospital-stay ranges, follow-up plan and operation-specific results. Request survival for your baby’s risk group, reoperation, infection, unplanned-transfer, ventilation and ICU-duration data—not a generic success rate.
2. Before choosing an infant cardiac surgery hospital, confirm continuous paediatric cardiac intensive-care coverage, mechanical ventilation, paediatric anaesthesia, blood-bank access and an emergency transfer pathway. Ask who provides follow-up after discharge and who calls you with urgent changes.
3. Get feeding and fasting instructions in writing. They must match your baby’s age, breast milk or formula feed, anaesthetic plan and operation time. Report poor feeding or heart-failure symptoms; ask the dietitian for a nutrition plan rather than guessing or withholding feeds.
Bedside nurses teach medicines and preparation; the physiotherapist supports breathing and movement; the counsellor addresses distress; and the social worker helps with transport, accommodation and practical needs. Ask who coordinates these professionals and whether translated consent support is available.
Who coordinates care before admission and during the hospital stay?
A defined care coordinator should be your route from admission to discharge, so you do not repeat the baby’s history to every department. Ask for that person’s name, direct number and backup contact before surgery.
1. The paediatric cardiologist explains the heart’s anatomy, test results and diagnosis. The paediatric cardiac surgeon explains the operation, alternatives and likely sequence of care.
2. The cardiac anaesthetist discusses anaesthesia, breathing support, intravenous and central lines, blood products and specific risks. The neonatal or paediatric intensivist prepares you for ventilation, monitoring and ICU routines.
3. Nurses organise medicines, hygiene, feeding and bedside teaching. The dietitian addresses nutrition; the physiotherapist covers safe handling and mobility; the counsellor supports emotional strain; and the social worker helps with accommodation, transport, finances and sibling care.
4. Name one primary family contact and record the hospital’s ward, ICU and overnight phone numbers. Ask who gives updates, how often, and whether an interpreter or translated consent information is available.
5. Before admission, confirm government-scheme eligibility, required documents, deposits, medicine costs and charges outside any package. For infant heart surgery care in Nagpur, ask which team handles follow-up and who answers urgent questions after discharge.
A coordinator should keep one shared record of medicines, allergies, investigations and consent discussions. That reduces delays and conflicting instructions when the baby moves between departments.
How do hospitals keep parents informed while the operation is underway?
Family support during infant surgery starts with a clear waiting plan. Ask where you will wait, who will call you, and whether updates are planned every hour, two hours, or at agreed milestones.
A nurse, coordinator, or surgeon’s representative may provide routine progress reports; a communication gap can last several hours during bypass, an unexpected problem, or transfer to intensive care, so agree on the maximum gap and an urgent-call number.
Before the operation, write down:
- The nominated family contact and the relatives allowed to receive updates
- The overnight phone number and who calls if the operation runs late
- How the hospital handles a change requiring fresh consent
- Interpreter access or translated consent information
- Visiting hours, hand-washing steps, masks, and infection-control restrictions
- Accommodation, meals, transport, phone charging, and financial-support contacts
- Where to label and refrigerate expressed breast milk, and who authorises its use
A waiting-room update is not the surgical explanation. Afterward, the paediatric cardiac surgeon should explain what was done, what changed, and what remains; the neonatal or paediatric intensive-care team should report the baby’s immediate condition, breathing support, lines, medicines, and next risks.
Parents usually cannot stay in the operating room because of sterility, anaesthesia equipment, and staff movement. Immediate touching or holding can also be unsafe while ventilation, invasive lines, drains, or infection precautions are in place. Ask how you can participate safely until bedside contact is allowed.
What will the ICU team do for breathing, monitoring and feeding?
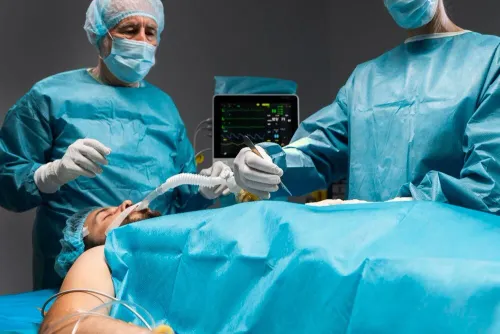
After a baby heart operation in Nagpur, breathing support and attached equipment are active treatment, not proof that recovery has failed. The ICU team explains what each device does, what change they are watching for and when they expect to remove it.
You may see:
- A ventilator through a breathing tube, or oxygen through prongs or a mask.
- Bedside monitors showing heart rate, oxygen level, blood pressure and breathing.
- Intravenous lines and a central line for fluids, medicines and nutrition.
- Chest drains removing air or fluid after surgery.
- A urinary catheter measuring urine output.
- Temporary pacing wires supporting the heart rhythm.
- Pain medicines, with swelling around the face or body during recovery.
- An open chest covered with a sterile dressing after selected high-risk operations, followed by closure when swelling and circulation improve.
An alarm needs staff assessment. Do not interpret it, silence it, reposition equipment or change settings; call the nurse and let the team check the baby.
Express breast milk as instructed, and label each container with the baby’s name, date and time. Staff will provide storage rules and prepare formula using the hospital’s measurements. Some babies receive measured feeds through a tube until the team decides that breast or oral feeding is safe to restart.
Tell the nurse if your baby has:
- Coughing or choking during a feed
- Vomiting, increasing fatigue or abdominal swelling
- Poor intake or fewer wet nappies
Never force a feed to meet a target.
How should a hospital prepare your family for discharge and long-term follow-up?
Before discharge, you should leave with a written plan, not verbal instructions remembered under stress. Ask the team to watch you give medicines, measure temperature, clean the wound and prepare a feed.
1. Take home a written medication schedule naming each drug, dose, timing, duration, medicine source and storage instructions. It must say whom to call after a missed dose or vomiting, and explain oxygen flow, monitoring and cylinder replacement when oxygen is prescribed.
2. Get the feeding plan in writing, including breast or formula feeds, quantities, tube-feeding instructions and the target number of wet nappies. Seek urgent help for breathing difficulty, blue or grey colour, collapse, sharply reduced feeding, fewer wet nappies, persistent vomiting, fever, wound redness or discharge, or unusual sleepiness.
Use a lower threshold for a young infant or a baby sent home on oxygen or complex medicines.
3. Confirm follow-up dates and responsibility before leaving. The pathway should review weight and growth, feeding and lactation, neurodevelopment, hearing, vision, physiotherapy and emotional wellbeing after a prolonged ICU stay, rather than treating surgery as the end of care.
4. When comparing infant cardiac surgery for hospital support in Nagpur, ask for operation- and risk-group-specific survival, reoperation, unplanned-transfer and infection rates, ventilation and ICU duration, follow-up ownership and emergency access. Ask Dr K G Deshpande Memorial Centre about its paediatric cardiac pathway and support services; a general service listing does not prove suitability.
Related product
 | Beating Heart Bypass Surgery / Completion Angiography MICS CABG / OPCAB / Small Incision Cardiac Surgery Valve Surgery Vascular Surgery Thoracic... View product → |
Frequently asked questions
What support should begin when your baby is referred for cardiac surgery?
Support should begin at referral with diagnostic confirmation, a written treatment plan and a named hospital contact. Ask when tests, specialist consultations and admission decisions will happen.
Who coordinates care before admission and during the hospital stay?
Ask which nurse, coordinator or doctor handles appointments, test results, admission arrangements and family questions. Confirm who will update you if the schedule or treatment plan changes.
How do hospitals keep parents informed while the operation is underway?
Ask how often the surgical team provides updates, who will contact you after major milestones and where you should wait. Confirm whom to call if you leave the waiting area.
What will the ICU team do for breathing, monitoring and feeding?
The ICU team monitors heart rhythm, blood pressure, oxygen levels, temperature and urine output. Ask about ventilation, pain control, feeding through a tube or breast and bottle-feeding, and the signs that show recovery is progressing.
How should a hospital prepare your family for discharge and long-term follow-up?
Before discharge, obtain written medicine doses and times, wound-care instructions, activity guidance, warning signs, emergency numbers and follow-up dates. Ask which cardiology tests and appointments your baby needs after leaving hospital.
Keywords